All published articles of this journal are available on ScienceDirect.

Systemic Sclerosis and Abortion: Determining Factors and Clinical Significance in a Multicenter Study
 iD
Authors Info & Affiliations
Abstract
Objective
The aim of this work was to identify disease-related factors associated with a history of spontaneous abortion in adult female patients with systemic sclerosis (SSc), and to further analyze the distinguishing features of SSc patients with recurrent versus single abortion episodes.
Materials and Methods
This multicenter case-control study was extracted from a nationwide SSc cohort of 1,080 patients. Ninety-one female adult SSc patients (8.4%) with a history of spontaneous abortion before 20 completed weeks of gestation were compared with 91 age-matched female SSc patients without a history of spontaneous abortion. Clinical characteristics, comorbidities, organ involvement, medications, and laboratory parameters were analyzed.
Results
Patients with spontaneous abortion had significantly longer disease duration (6.4±4.7 vs. 4.6±4.2 years; p=0.007), a higher prevalence of comorbidities (29.7% vs. 15.4%; p=0.03), more frequent telangiectasia (28.6% vs. 12.1%; p=0.009) and a higher frequency of mycophenolate mofetil use (29.7% vs. 15.4%; p=0.03) compared with patients without a history of spontaneous abortion. Recurrent spontaneous abortion occurred in 30 patients (33.0%). Compared with those with a single spontaneous abortion, patients with recurrent spontaneous abortion had significantly higher frequencies of Raynaud’s phenomenon (p<0.0001), hand puffiness (p=0.047), hypo-/hyperpigmentation (p=0.03), cardiovascular involvement (p=0.046), anti-Scl-70 positivity (p=0.01), double autoantibody positivity (p=0.017), and higher serum triglyceride levels (p=0.006).
Discussion
Patients with SSc have a higher risk of spontaneous abortion than the general population; this risk is likely driven by decidual vasculopathy and fibrosis. Factors contributing to spontaneous abortion were variable in previous reports, with hypertension and long disease duration among the most contributing factors.
Conclusion
In women with SSc, spontaneous abortion is associated with longer disease duration, telangiectasia, higher serum creatinine levels, the presence of comorbidities, and the use of MMF. Recurrent spontaneous abortion is associated with anti-Scl-70 positivity, double autoantibody positivity, and hypertriglyceridemia.
1. INTRODUCTION
Systemic Sclerosis (SSc) is a multifactorial autoimmune disease; its pathological hallmark is characterized by progressive fibrosis and vasculopathy. The overall global incidence is 1:10,000. The incidence in women is 4- 9 times higher than in men [1]. This female predominance is even higher during the reproductive period (15–50 years), where females have a 15-fold increase in the incidence of the disease compared to males [2]. Vascular abnormalities are a key driver of disease progression [3]. Whereas fertility may not be reduced in women with SSc [4], pregnancy increases the risk of organ involvement, system dysfunction, and carries risks to the fetus [5].
Diffuse subtype, anti-topoisomerase 1 or anti-RNA polymerase 3 antibodies carry a greater obstetric risk [6]. Complications include hypertension, renal failure, pulmonary hypertension (PAH), interstitial lung disease (ILD), and heart failure, which are usually seen starting from the second trimester of pregnancy [7]. Women with preclinical SSc have higher frequencies of adverse pregnancy outcomes preceding the diagnosis [8, 9]. Similar patterns have been shown in women with other rheumatic diseases (RDs) [10].
The risk of abortion in SSc is controversial, while previous reports found a higher risk of abortion in SSc patients compared to the general population [8, 11, 12]; others found the risk comparable to the general population. In a meta-analysis published in 2020, pregnancies in women with SSc had a higher risk of abortions compared with healthy controls (OR 1.6, 95% CI 1.22–2.22) [13]. Contrarily, other studies suggest that the risk of abortion in SSc women can be controlled when closely monitored [14-16], except for patients with severe diffuse SSc who may experience a higher risk for miscarriage [15]. Severe internal organ involvement (PAH, active Scleroderma Renal Crisis (SRC), severe ILD) represents a near-fatal risk and is the most determining factor for poor outcome. Patients developing SRC necessitated an elective abortion at 19 weeks; similarly, PAH represented a high risk to the mother and the fetus, leading in most cases to elective medical termination [17].
Placental vasculopathy has been observed in SSc, yet the significance of this pathology in inducing abortion in SSc is still unknown [4]. Histopathological analysis of placental biopsies revealed marked decidual vasculopathy, which, when correlated with fetal outcomes, was significantly associated with fetal demise between gestational weeks 16 and 30 [18]. Additional findings included chorioamnionitis and accelerated placental maturation; these histological patterns parallel those observed in pregnancies complicated by pregnancy-induced hypertension. Notably, placental abnormalities may manifest in SSc pregnancies even in the absence of clinical perinatal complications. However, the severity of placental vascular pathology is directly proportional to the risk of spontaneous abortion, Intrauterine Growth Restriction (IUGR), and preterm delivery [19].
A well-timed pregnancy with careful obstetric monitoring will increase the probability of a successful outcome [15]. It has been advised that pregnancy should be delayed in patients with early disease (<4 years), as patients in early disease showed higher rates of miscarriages [20].
Although previous studies have described pregnancy outcomes in women with systemic sclerosis, data evaluating the clinical, serological, and metabolic factors associated with a lifetime history of spontaneous abortion and recurrent spontaneous abortion in large multicenter cohorts remain limited. Therefore, this study aimed to identify the demographic, clinical, laboratory, serological, and treatment-related factors associated with spontaneous abortion in women with systemic sclerosis and to explore potential predictors of recurrent pregnancy loss.
2. MATERIALS AND METHODS
2.1. Study Design and Setting
This is a multicenter, age-matched, case-control observational study cohort of scleroderma patients nested within a large nationwide cohort of 1,080 SSc cases [21]. The study was conducted across specialized rheumatology centers in Egypt over a period of 1 year, spanning from March 2024 to March 2025.
2.2. Participants and Study Size
A total of 1,080 patients from the nationwide SSc cohort were initially screened for eligibility. Of these, 898 were excluded due to male sex or incomplete obstetric data. A total of 182 female adult participants were included in this study. We identified 91 cases (8.4%) with a documented history of abortion. A history of spontaneous abortion was defined as one or more spontaneous pregnancy losses before 20 completed weeks of gestation occurring at any time during the patient's reproductive life, irrespective of whether the pregnancy occurred before or after the diagnosis of systemic sclerosis. These were compared to a control group of 91 age-matched adult female patients with systemic sclerosis who had no history of spontaneous abortion in a 1:1 ratio. The mean age of participants was 42±10.1.
2.3. Inclusion and Exclusion Criteria
2.3.1. Inclusion Criteria are as Follows:
- Female adult patients (≥18 years).
- Confirmed diagnosis of SSc fulfilling the 2013 ACR/EULAR classification criteria [22].
- Complete clinical and obstetric data available in the standardized electronic database.
2.4. Data Collection and Variables
Clinical and laboratory data were retrieved using a standardized electronic database. Obstetric history, including the occurrence and number of spontaneous abortions, was obtained from the standardized nationwide electronic systemic sclerosis database, which was completed by the treating rheumatologists using patients' medical records. Variables analyzed included disease duration, SSc subtype, presence of Raynaud’s phenomenon, telangiectasia, digital ulcers, and organ involvement (renal, cardiovascular, and pulmonary). Laboratory markers, including serum creatinine, triglycerides, and autoantibody profiles (Anti-Scl-70, ACA), were recorded. Pharmacological history, specifically the use of Calcium Channel Blockers (CCBs), Methotrexate (MTX), Mycophenolate Mofetil (MMF), and biologic therapies, was also extracted to evaluate its association with pregnancy outcomes.
The initial study protocol was approved by the ethical committee of the University of Sohag, Egypt [Soh-Med-25-8-3PD] and conducted in accordance with the Declaration of Helsinki. Informed consent was obtained from all participants.
2.5. Bias
To minimize selection bias, all cases and controls were recruited from the same nationwide database using standardized ACR/EULAR 2013 diagnostic criteria. Information bias was addressed by utilizing a standardized electronic database, which ensured consistent data collection across different centers. To reduce confounding bias, cases (SSc with abortion) were matched 1:1 with controls (SSc without abortion) based on age, a primary factor influencing pregnancy outcomes.
2.6. Study Size
The study size was determined by the total number of eligible female patients within the nationwide cohort (n=1080) who had documented pregnancy histories. Out of the total cohort, all 91 patients meeting the criteria for a history of abortion were included as cases. An equal number of controls (n=91) were selected via age-matching to ensure a balanced 1:1 ratio, maximizing statistical power for the comparative analysis within the available dataset.
2.7. Quantitative Variables
Quantitative variables, such as disease duration and serum creatinine levels, were initially analyzed as continuous data to assess their distribution using the Kolmogorov-Smirnov test. Because these variables were non-normally distributed, they were compared using non-parametric tests (Mann-Whitney U). For clinical utility, these variables were further handled as follows:
- Categorical Grouping: Disease duration was categorized into “early disease” (<4years) and “established disease” based on clinical significance for renal crisis risk.
- ROC Analysis: Optimum cut-off points for creatinine and disease duration were determined using Receiver Operating Characteristic (ROC) curves to transform continuous data into predictive binary markers for abortion risk.
2.8. Statistical Analysis
Statistical analysis was conducted using IBM SPSS Statistics software (version 25).
2.8.1. Descriptive Statistics
Continuous variables were expressed as mean ± standard deviation (SD) and range, while categorical variables were presented as frequencies and percentages.
2.8.2. Comparative Analysis
To evaluate differences between cases (history of abortion) and controls, the Chi-square test (or Fisher’s exact test, where appropriate) was utilized for categorical data. For continuous variables, the Mann–Whitney U test was used to compare two groups, and the Kruskal-Wallis test was applied for comparisons involving more than two groups, as the data followed a non-parametric distribution.
3. RESULTS
3.1. Participant Flow and Selection
A total of 1,080 patients from the nationwide SSc cohort were initially screened for eligibility.
Of these, 898 were excluded due to male sex or incomplete obstetric data. Among the remaining eligible female population, 91 patients (8.4%) were identified with a history of abortion and included as cases. To ensure comparability, 91 age-matched SSc patients without a history of abortion were selected as controls. All 182 participants were included in the final analysis.
3.2. Descriptive Data and Exposures
The clinical and demographic characteristics of the 182 participants are detailed in Tables 1 and 2.
|
Parameters mean±SD, n (%) |
Female SSc patients with and without abortion (n=182) | |||
|---|---|---|---|---|
| All (n=182) | with (n=91) | without (n=91) | p | |
| Age (years) | 42±10.1 | 43±9.6 | 41±10.6 | 0.17 |
| Disease duration (y) | 5.5±4.5 | 6.4±4.7 | 4.6±4.2 | 0.007 |
| Age at onset (y) | 36.5±9.5 | 36.9±8.5 | 36.1±10.4 | 0.55 |
| Smoking | 5 (2.7) | 5 (5.5) | 0 (0) | - |
| Family hx of RD | 11 (6) | 4 (4.4) | 7 (7.7) | 0.54 |
| Subtype: lcSSc | 40 (22) | 25 (27.5) | 15 (16.5) | 0.14 |
| dcSSc | 114 (62.6) | 51 (56) | 63 (69.2) | |
| overlap | 32 (17.6) | 15 (16.5) | 13 (14.3) | |
| Co-morbidities | 41 (22.5) | 27 (29.7) | 14 (15.4) | 0.03 |
| Diabetes | 18 (9.9) | 11 (12.1) | 7 (7.7) | 0.46 |
| Hypertension | 22 (12.1) | 15 (16.5) | 7 (7.7) | 0.11 |
| Thyroid disorder | 17 (9.3) | 11 (12.1) | 6 (6.6) | 0.31 |
| Clinical manifestations | ||||
| Raynauds | 139 (76.4) | 62 (68.1) | 77 (84.6) | 0.014 |
| Pitting scar | 61 (33.5) | 25 (27.5) | 36 (39.6) | 0.12 |
| Digital ulcers | 71 (39) | 33 (36.3) | 38 (41.8) | 0.54 |
| Hand puffiness | 52 (28.6) | 26 (28.6) | 26 (28.6) | 1 |
| Arthralgia | 81 (44.5) | 50 (54.9) | 31 (34.1) | 0.007 |
| Arthritis | 66 (36.3) | 33 (36.3) | 33 (36.3) | 1 |
| Hypo/hyperpigmentation | 47 (25.8) | 28 (30.8) | 19 (20.9) | 0.18 |
| Chest | 114 (62.6) | 53 (58.2) | 61 (67) | 0.28 |
| Gastrointestinal | 104 (57.1) | 53 (58.2) | 51 (56) | 0.88 |
| Fish mouth | 51 (28) | 23 (25.3) | 28 (30.8) | 0.51 |
| Telangiectasia | 37 (20.3) | 26 (28.6) | 11 (12.1) | 0.009 |
| Neurological | 24 (13.2) | 13 (14.3) | 11 (12.1) | 0.83 |
| Renal | 15 (8.2) | 11 (12.1) | 4 (4.4) | 0.1 |
| Cardiovascular | 53 (29.1) | 24 (26.4) | 29 (31.9) | 0.51 |
| PAH | 41 (22.5) | 21 (23.1) | 20 (22) | 1 |
| mRss | 16.9±9.5 | 15.1±8.7 | 19.4±10.2 | 0.08 |
|
Parameters mean±SD, n (%) |
SSc patients with and without abortion (n=182) | |||
|---|---|---|---|---|
| All (n=182) | with (n=91) | without (n=91) | p | |
| Investigations | ||||
| Hemoglobin | 11.3±1.6 | 11.3±1.6 | 11.3±1.7 | 0.97 |
| TLC | 7.02±3.1 | 6.7±3.02 | 7.3±3.2 | 0.19 |
| Platelets | 285.8±92.8 | 277.7±99.6 | 293.7±85.4 | 0.26 |
| ESR | 45±25.2 | 46.7±27.6 | 43.1±22.6 | 0.37 |
| Creatinine | 0.85±0.43 | 0.94±0.52 | 0.75±0.27 | 0.004 |
| ALT | 23.3±10.2 | 22.4±10 | 24.3±10.4 | 0.26 |
| AST | 24.1±10.4 | 23.7±9.9 | 24.6±11.04 | 0.59 |
| Cholesterol | 222±70.2 | 223.3±73.2 | 216.4±58.8 | 0.78 |
| Triglycerides | 138.1±74.1 | 131.4±74.3 | 164±71.1 | 0.25 |
| RF | 21 (11.5) | 13 (14.3) | 8 (8.8) | 0.26 |
| ANA | 100 (54.9) | 51 (56) | 49 (53.8) | 0.88 |
| dsDNA | 6 (3.3) | 3 (3.3) | 3 (3.3) | 1 |
| Anti-Scl-70 | 53 (29.1) | 32 (35.2) | 21 (23.1) | 0.1 |
| Anti-centromere | 37 (20.3) | 24 (26.4) | 13 (14.3) | 0.06 |
| Double-positivity | 25 (13.7) | 16 (17.6) | 9 (9.9) | 0.19 |
| Medications | ||||
| Steroids | 101 (55.5) | 52 (57.1) | 49 (53.8) | 0.77 |
| CCB | 48 (26.4) | 21 (23.1) | 27 (29.7) | 0.008 |
| Pentoxyphylline | 80 (44) | 35 (38.5) | 45 (49.5) | 0.17 |
| HCQ | 60 (33) | 35 (38.5) | 25 (27.5) | 0.16 |
| MTX | 70 (38.5) | 27 (29.7) | 43 (47.3) | 0.02 |
| Sildinafil | 43 (23.9) | 18 (19.8) | 25 (27.5) | 0.29 |
| AZA | 47 (25.8) | 26 (28.6) | 21 (23.1) | 0.5 |
| LFN | 24 (13.2) | 14 (15.4) | 10 (11) | 0.51 |
| CYC | 29 (15.9) | 17 (18.7) | 12 (13.2) | 0.42 |
| MMF | 41 (22.5) | 27 (29.7) | 14 (15.4) | 0.03 |
| Biologic | 11 (6) | 7 (7.7) | 4 (4.4) | 0.54 |
3.2.1. Abortion Frequency
In the case group (n=91), 67% (n=61) reported a single abortion, while 33% (n=30) experienced recurrent abortions (range: 2–4).
3.3. Main Results
Patients with a history of spontaneous abortion had a significantly longer disease duration than those without spontaneous abortion (6.4±4.7 vs. 4.6±4.2 years, p=0.007). They also had a significantly higher frequency of comorbidities (29.7% vs. 15.4%, p=0.03), arthralgia (54.9% vs. 34.1%, p=0.007), and telangiectasia (28.6% vs. 12.1%, p=0.009). Conversely, Raynaud's phenomenon was significantly less frequent among patients with spontaneous abortion than among controls (68.1% vs. 84.6%, p=0.014). (Table 1).
Regarding laboratory investigations, patients with spontaneous abortion had significantly higher serum creatinine levels than those without spontaneous abortion (0.94±0.52 vs. 0.75±0.27 mg/dL, p=0.004). (Table 2).
With respect to treatment, mycophenolate mofetil was prescribed significantly more frequently in patients with spontaneous abortion than in controls (29.7% vs. 15.4%, p=0.03), whereas methotrexate and calcium channel blockers were used more frequently in patients without spontaneous abortion (47.3% vs. 29.7%, p=0.02 and 29.7% vs. 23.1%, p=0.008, respectively (Table 2).
Among patients with a history of spontaneous abortion, those with recurrent spontaneous abortion had significantly higher frequencies of Raynaud's phenomenon (93.3% vs. 55.7%, p<0.0001), hand puffiness (43.3% vs. 21.3%, p=0.047), hypo-/hyperpigmentation (46.7% vs. 23.0%, p=0.03), cardiovascular involvement (40.0% vs. 19.7%, p=0.046), anti-Scl-70 positivity (53.3% vs. 26.2%, p=0.01), and double antibody positivity (33.3% vs. 9.8%, p=0.017). They also had significantly higher serum triglyceride levels (188.7±86.4 vs. 101.6±45.6 mg/dL, p=0.006) and were more frequently receiving calcium channel blockers (66.7% vs. 31.1%, p=0.003), sildenafil (33.3% vs. 13.1%, p=0.048), azathioprine (43.3% vs. 21.3%, p=0.047), leflunomide (33.3% vs. 6.6%, p=0.002), and cyclophosphamide (36.7% vs. 9.8%, p=0.004) (Table 3).
|
Parameters mean±SD, n (%) |
Female SSc patients with abortion (n=91) | |||
|---|---|---|---|---|
| with (n=91) | Once (n=61) | Recurrent (n=30) | p | |
| Clinical manifestations | ||||
| Raynauds | 62 (68.1) | 34 (55.7) | 28 (93.3) | <0.0001 |
| Hand puffiness | 26 (28.6) | 13 (21.3) | 13 (43.3) | 0.047 |
| Hypo/hyperpigmentation | 28 (30.8) | 14 (23) | 14 (46.7) | 0.03 |
| Cardiovascular | 24 (26.4) | 12 (19.7) | 12 (40) | 0.046 |
| Investigations | ||||
| Triglycerides | 131.4±74.3 | 101.6±45.6 | 188.7±86.4 | 0.006 |
| Anti-Scl-70 | 32 (35.2) | 16 (26.2) | 16 (53.3) | 0.01 |
| Double-positivity | 16 (17.6) | 6 (9.8) | 10 (33.3) | 0.017 |
| Medications | ||||
| CCB | 21 (23.1) | 19 (31.1) | 20 (66.7) | 0.003 |
| Sildinafil | 18 (19.8) | 8 (13.1) | 10 (33.3) | 0.048 |
| AZA | 26 (28.6) | 13 (21.3) | 13 (43.3) | 0.047 |
| LFN | 14 (15.4) | 4 (6.6) | 10 (33.3) | 0.002 |
| CYC | 17 (18.7) | 6 (9.8) | 11 (36.7) | 0.004 |
Receiver Operating Characteristic (ROC) curve analysis demonstrated that a disease duration greater than 3.5 years predicted spontaneous abortion with an Area Under the Curve (AUC) of 0.662 (95% CI, 0.58–0.75), a sensitivity of 72.8%, and a specificity of 54.5% (p<0.0001). Similarly, a serum creatinine level greater than 0.8 mg/dL predicted spontaneous abortion with an AUC of 0.63 (95% CI, 0.54–0.72), a sensitivity of 60.5%, and a specificity of 67.5% (p=0.005) (Figure 1).
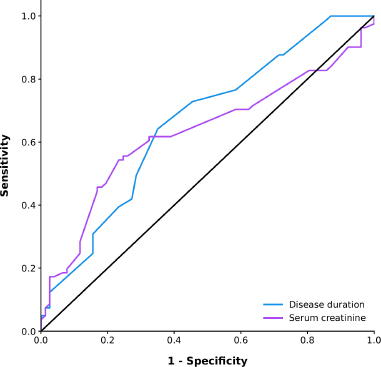
Receiver operating characteristic (ROC) curve showing significant predictive potential of developing abortion in systemic sclerosis (SSc) patients with disease duration at cut-off >3.5 years (AUC =0.662, CI95% 0.58-0.75, sensitivity 72.8% and specificity 54.5%, p<0.0001) and serum creatinine level at cut-off > 0.8 mg/dl (AUC =0.63, CI95% 0.54-0.72, sensitivity 60.5% and specificity 67.5%, p=0.005)
For recurrent spontaneous abortion, a serum triglyceride level greater than 80 mg/dL predicted recurrence with an AUC of 0.784 (95% CI, 0.61–0.96), a sensitivity of 83.3%, and a specificity of 34.8% (p=0.006) (Figure 2).
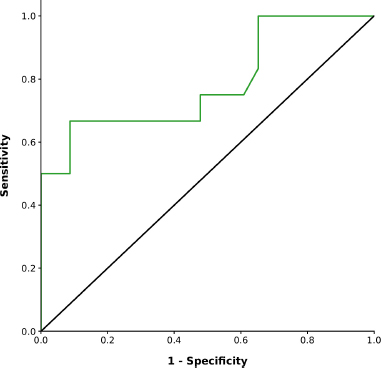
Receiver operating characteristic (ROC) curve showing significant predictive potential of developing recurrent abortion in systemic sclerosis (SSc) patients with serum triglycerides at cut-off > 80 mg/dl (AUC =0.784, CI95% 0.61-0.96, sensitivity 83.3% and specificity 34.8%, p=0.006).
4. DISCUSSION
Like many autoimmune diseases, SSc occurs more frequently in women and is relatively common during childbearing age. Women with SSc may have successful pregnancies, although there is an increased occurrence of adverse pregnancy outcomes including abortion, preterm birth, small for gestational age, and low birth weight [10]. The need for modern studies to address whether the risk of adverse outcomes has decreased over time is warranted given improved rheumatologic and obstetric management [23]. To date, literature data on pregnancy outcomes in women with SSc are lacking [24].
The cause of spontaneous abortion in SSc is not fully understood. Pathogenesis is thought to involve autoimmunity, fibrosis, collagen production, and vasculopathy. SSc involves various internal organs, and the placenta may be affected with decidual vasculopathy that may induce ischemia associated with a poor pregnancy outcome [25]. The rate of abortion is higher when pregnancy occurs after the onset of the disease compared to those prior to onset of SSc (15% vs 11%) [20]. Moreover, the overall rate of miscarriage in SSc (12-15% of pregnancies) is higher than in the general population (11% of pregnancies) [26]. In a study from Spain, abortion was higher in SLE patients (22%), followed by SSc (18%), primary Sjögrens disease (15%) and undifferentiated connective tissue disease (UCTD) (15%) [27]. In Portugal, 16.7% of SSc patients had miscarriage [28]. Out of 111 SSc women from the USA (248 pregnancies), 19.8% of patients had 12.9% spontaneous abortions [29].
In the current work, the disease duration was significantly longer in SSc patients with a history of abortion. In agreement, the risk of abortion was reported to increase with disease duration [15].
We found that co-morbidities including hypertension, diabetes and thyroid dysfunction were significantly more frequent in patients with abortion. Women with SSc exhibit a heightened susceptibility to pregnancy complications, such as gestational hypertension, mandating a high-risk approach to obstetrical care [15]. In a large-scale US study, the risk of fetal mortality among women with SSc demonstrated a marked improvement over the last two decades. Nevertheless, SSc deliveries continued to present a significantly higher risk for adverse pregnancy outcomes, including hypertensive disorders, compared to controls; this disparity warrants the implementation of specific clinical strategies to improve outcomes [30]. Similarly, a nationwide Swedish registry reported that while SSc pregnancies were associated with an increased risk of preeclampsia, this did not translate to higher rates of maternal death, neonatal death, or stillbirth [10].
The subtype of SSc had no influence on the frequency of abortion in our study; however, the rate of limited cutaneous systemic sclerosis (lcSSc) was significantly higher in those with abortion. However, an early study revealed that diffuse cutaneous systemic sclerosis (dcSSc) is associated with a higher risk of abortion [15]. A healthy successful pregnancy and outcome are possible for SSc women. Patients with early disease (less than 4 years' duration) and progressive diffuse skin thickening should avoid pregnancy as they are at higher risk of developing renal crisis [31].
Although the frequency of adverse pregnancy outcomes was generally higher in those with dcSSc compared to those with lcSSc (100% vs 53%), miscarriage was reported only in those with lcSSc [31]. Others reported that the subtype had no significant effects on the pregnancy outcomes after the disease onset [32]. In a nationwide study from the USA, out of 111 SSc women with complete pregnancy history, 19.8% of patients had spontaneous abortion; 45% had dSSc, while lcSSc was present in 55% [29].
A recent prospective cohort reported that although over 90% of pregnancies in women with systemic sclerosis resulted in live births, these pregnancies remained associated with increased rates of pre-eclampsia, preterm delivery, fetal growth restriction, low birthweight, and severe postpartum hemorrhage compared with the general population. Moreover, nearly 40% of women experienced disease progression, predominantly during the postpartum period. The major risk factors were dcSSc and previous cutaneous vascular involvement [33].
The frequency of Raynaud’s was significantly lower in the current patients with a history of abortion, perhaps shedding light on the importance of conducting a prospective study to monitor the increase in frequency over the following months and years. In SLE cases, abortions were not increased in patients with Raynaud’s phenomenon regardless of the presence of a positive anticardiolipin antibody [34]. The occurrence of miscarriage, stillbirth, and small gestational age infants was similarly found in patients with primary Raynaud’s phenomenon and controls [35].
In the present study, telangiectasia was significantly increased in those with a history of abortion. Telangiectasia may theoretically be a clue to complications during pregnancy such as miscarriages and abortions. However, this hypothesis was not studied in patients with SSc.
The serum creatinine level in patients with abortion was significantly higher than in those without. Scleroderma Renal Crisis (SRC) is a major vascular life-threatening complication of SSc and is associated with high morbidity and mortality, defined by an increased serum creatinine level [36]. It is stated that more than half of SSc patients have asymptomatic renal involvement such as proteinuria, elevated creatinine level, and hypertension [37].
The patients in this study without abortion were receiving a significantly higher frequency of Calcium Channel Blockers (CCBs) and methotrexate (MTX), signifying better control of the disease status, while receiving biologic therapy tended to be higher in those with abortion. Similarly, women with rheumatoid arthritis (RA) who were taking MTX had a lower rate of induced abortions than unexposed women, while the contrary was found in those who took anti-TNF as compared to those unexposed; the patients who took anti-TNF agents had an increased rate of induced abortions [38].
In the present study, the frequency of patients receiving MMF was significantly higher in SSc patients with a history of abortion. MMF is an established therapy in SSc with a potential efficacy against skin and lung fibrosis. The contribution of medications to obstetric risk could not be adequately evaluated because of the retrospective study design and the absence of detailed pregnancy-specific treatment data. Consequently, the observed associations between medication use and spontaneous abortion may reflect underlying disease severity rather than a direct effect of the medications themselves. Thus, these results may be interpreted as suggesting that these SSc patients had major organ involvement requiring MMF therapy and thus increasing the risks for abortion.
A previous study demonstrated that pregnancy outcomes change markedly according to systemic sclerosis disease activity. Women with active or early disease experienced frequent disease exacerbations during or shortly after pregnancy, higher rates of hypertensive disorders, fetal loss, and intrauterine growth restriction/low birthweight. In contrast, women with stable disease had planned pregnancies with close monitoring, remained clinically stable throughout pregnancy, and had substantially better maternal and fetal outcomes, although low birthweight remained relatively common [39].
Patients with recurrent abortion had a significantly higher frequency of Raynaud’s, hand puffiness, hypo/hyperpigmentation, cardiovascular disease, anti-Scl-70 and double positivity, as well as of receiving CCB, sildenafil, azathioprine, leflunomide and cyclophosphamide compared to those with a single abortion. The serum level of triglycerides was significantly higher than that of those with recurrent abortion. Although the ROC analysis showed low specificity (34.8%), it sheds light on the altered lipid profile in these patients and the need for early detection and management of hypertriglyceridemia. The frequency of adverse pregnancy outcomes was significantly higher in SSc women (60%) compared to SLE (37.5%), anti-phospholipid syndrome (36.6%), or to the normal subjects (10%), with a higher rate of miscarriage [24]. Accordingly, pregnant women with SSc face an elevated risk of adverse obstetrical outcomes. Specifically, rates of spontaneous abortion in this cohort exceed those observed in both the general population and patients with SLE, necessitating a high-risk, multidisciplinary management approach [24]. Conversely, evidence suggests that experiencing multiple pregnancies following an SSc diagnosis does not significantly compromise long-term renal, respiratory, or global functional outcomes. While these findings offer reassurance for patients considering pregnancy, clinicians must remain vigilant regarding potential postpartum complications to optimize the clinical care provided for these women [40].
Preconception counseling, risk stratification, and multidisciplinary management are of utmost importance in these groups of patients. Personalized approaches and shared decisions minimize overall maternal and fetal risks [41, 42].
5. LIMITATIONS
The Retrospective Design, as an observational study extracting data from an electronic database, carries an inherent risk of recall bias or missing documentation regarding past obstetric history, which may lead to an underestimation of early spontaneous abortions. In addition, the contribution of medications to obstetric risk could not be adequately evaluated because of the lack of detailed pregnancy-specific treatment data. Therefore, the observed associations between medication use and spontaneous abortion should be interpreted with caution, as they may reflect underlying disease severity rather than a direct effect of the medications.
5.1. Case-Control Nature
Although age-matching was performed to reduce confounding, the case-control design allows for the identification of associations rather than direct causality between SSc clinical markers and pregnancy loss.
5.2. Database Constraints
Some potential confounders, such as detailed smoking history, Body Mass Index (BMI) at the time of pregnancy, and specific antiphospholipid antibody titers (other than those routinely recorded), were not uniformly available for all patients.
Future research should prioritize prospective longitudinal studies to track SSc patients from preconception through the postpartum period, allowing for real-time monitoring of clinical and metabolic fluctuations. Investigating the histopathological mechanisms of decidual vasculopathy.
CONCLUSION
In conclusion, abortion in SSc patients is intimately related to the presence of telangiectasia, longer disease duration, higher serum creatinine levels, the presence of co-morbidities, and the use of MMF. Many factors determine the recurrence of abortion, with a higher level of triglycerides having a strong link.
AUTHORS’ CONTRIBUTIONS
The authors confirm their contribution to the paper as follows: G.T., S.A., A.F.: Conceived and designed the study; M.G. and N.N.: Performed the statistical analysis; E.R., A.N., M.E., A.E., T.S., A.K., M.T., B.A., A.Y. and E.G.: Responsible for patient recruitment, data collection, and clinical management; G.T. and E.N.: Wrote the first draft of the manuscript; H.N., E.I., E.A. and E.N.: Provided critical revision of the manuscript for important intellectual content. All authors contributed to the interpretation of the results and approved the final version for submission.
LIST OF ABBREVIATIONS
| CCBs | = Calcium Channel Blockers |
| dcSSc | = Diffuse cutaneous systemic sclerosis |
| ILD | = Interstitial Lung Disease |
| IUGR | = Intrauterine growth restriction |
| lcSSc | = Limited cutaneous systemic sclerosis |
| MMF | = Mycophenolate Mofetil |
| MTX | = Methotrexate |
| PAH | = Pulmonary hypertension |
| RDs | = Rheumatic diseases |
| SRC | = Scleroderma renal crisis |
| SSc | = Systemic sclerosis |
| UCTD | = Undifferentiated connective tissue disease |
ETHICS APPROVAL AND CONSENT TO PARTICIPATE
The initial study protocol was approved by the ethical committee of the University of Sohag, Egypt [Soh-Med-25-8-3PD].
HUMAN AND ANIMAL RIGHTS
All human research procedures followed were in accordance with the ethical standards of the committee responsible for human experimentation (institutional and national), and with the Helsinki Declaration of 1975, as revised in 2013.
AVAILABILITY OF DATA AND MATERIALS
The data are available from the corresponding author [N.Y.E.] on request.
ACKNOWLEDGEMENTS
The authors would like to express their sincere gratitude to all the patients who participated in this multicenter study. They also acknowledge the efforts of the rheumatology teams and data collectors across the participating centers for their valuable contributions to patient recruitment, clinical assessment, and data entry. The authors also thank the statistical support team for their assistance in data management and analysis.

